Overview
For the working professional community along the Ghodbunder Road corridor, interstitial cystitis and chronic bladder pain syndrome represent conditions that are particularly disruptive — the bladder pain that builds as the bladder fills interferes with meetings, travel, and the sustained professional focus that demanding roles require.Read moreShow less
Yet IC is among the most commonly mismanaged conditions in this community, because its symptoms — urgency, frequency, pelvic pressure — resemble OAB and are treated with antimuscarinics that have limited effect on a non-detrusor-overactivity condition. At Mercurrey Hospital in Kapurbawdi — accessible from Hiranandani Estate in 12 minutes — HRG Urology provides the specific IC diagnostic and treatment pathway: cystoscopy with hydrodistension, intravesical instillation therapy, and Botox injection where needed. Dr. Harshawardhan Godbole FRCS. ₹1,000.
What to know
Chronic Bladder Conditions at Mercurrey Hospital, Kapurbawdi
Chronic bladder conditions include interstitial cystitis (IC)/painful bladder syndrome (PBS), bladder pain syndrome, radiation cystitis, chemical cystitis, and chronic bladder wall thickening from longstanding inflammation.Read moreShow less
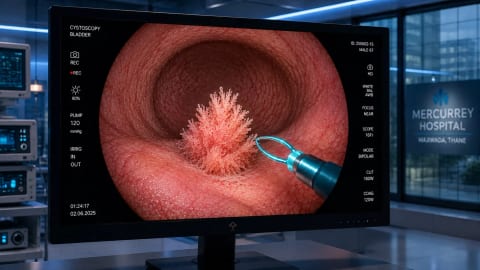
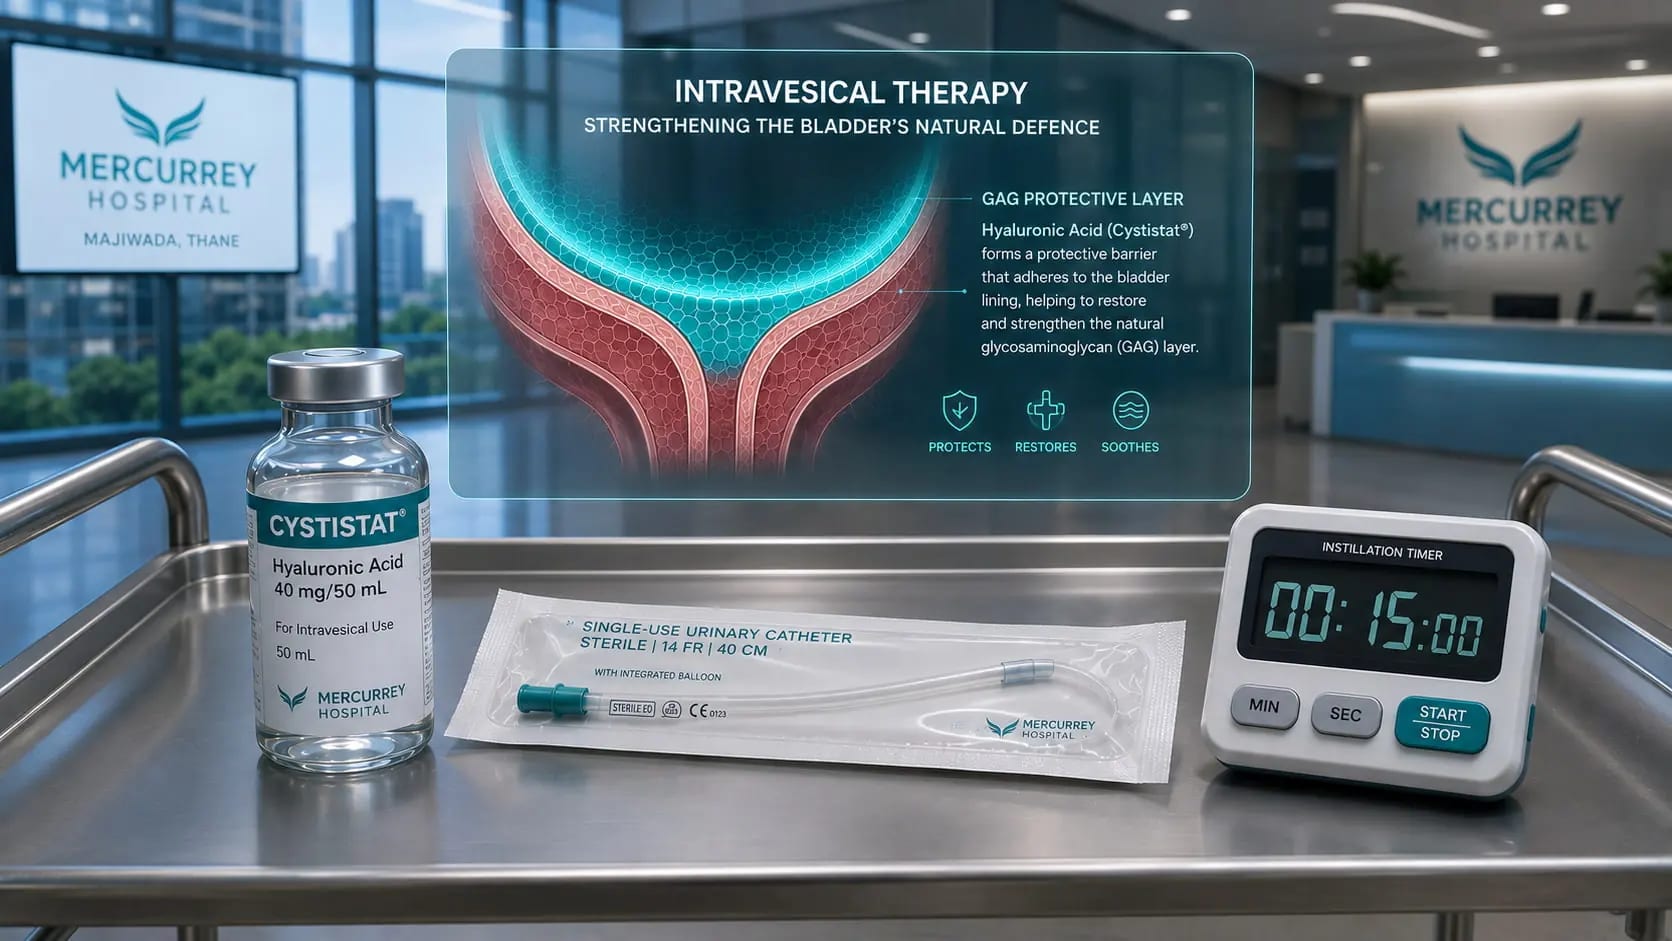
IC is characterised by bladder pain that increases as the bladder fills and is relieved by voiding, with urgency, frequency, and nocturia, in the absence of infection or identifiable pathology. Cystoscopy with hydrodistension and bladder biopsy confirms IC. Treatment: intravesical instillations (hyaluronic acid, chondroitin sulphate, BCG), oral pentosan polysulphate, tricyclic antidepressants for bladder pain, and botulinum toxin injection for refractory cases. All chronic bladder conditions require bladder cancer exclusion by cystoscopy before diagnosis.
IC Misdiagnosed as OAB in the Ghodbunder Road Professional Community
The Ghodbunder Road professional who has been prescribed antimuscarinics for "overactive bladder" without adequate response.Read moreShow less
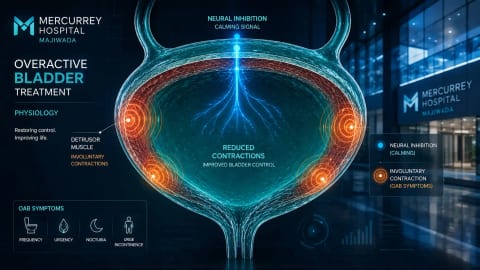
Particularly if bladder pain is the predominant symptom rather than urgency alone — may have IC rather than OAB. The distinction is clinically critical: antimuscarinics reduce detrusor overactivity but have limited effect on the bladder wall pain of IC, while intravesical instillations that target the GAG layer provide no benefit for OAB. At Mercurrey Hospital, patients with persistent bladder symptoms despite antimuscarinic therapy are assessed for IC with cystoscopy before the next OAB treatment tier is applied — preventing months of misdirected escalation.
IC and Sexual Function — An Underaddressed Aspect of Chronic Bladder Pain
IC causes significant sexual dysfunction in women.Read moreShow less
Dyspareunia (pain during intercourse) is common due to pelvic floor hypertonicity and bladder wall sensitivity. This sexual function impact is rarely addressed in standard IC management, yet it is often the most distressing aspect of the condition for affected women. At Mercurrey Hospital, Dr. Godbole's IC assessment specifically includes the sexual function history and, where dyspareunia is a significant component, coordinates referral to pelvic floor physiotherapists alongside the instillation treatment programme.
Travel and Parking Guide – Mercurrey Hospital, Kapurbawdi
High Street Mall Junction, Samata Nagar, Kapurbawdi, Majiwada 400607.Read moreShow less
From Hiranandani Estate: 10–12 minutes. From Manpada: 15 minutes. From Brahmand: 20 minutes. Auto-rickshaws know "Kapurbawdi High Street Mall." Street parking at the junction.
Why Mercurrey
Ghodbunder Road patients with chronic bladder symptoms choose Mercurrey Hospital because the Kapurbawdi location is 10–20 minutes from their homes.Read moreShow less
Making the weekly instillation appointments that IC treatment requires manageable around professional schedules.
The OAB-versus-IC distinction at Mercurrey Hospital.Read moreShow less
Assessed by cystoscopy with hydrodistension when antimuscarinic response is inadequate — prevents the months of misdirected OAB escalation that continues when IC is the actual diagnosis.
The sexual function impact of IC.Read moreShow less
Particularly dyspareunia — is addressed in the assessment at Mercurrey Hospital, with pelvic floor physiotherapy referral coordinated alongside instillation therapy for women where this is a significant component.
Nearby areas
MajiwadaKapurbawdiGhodbunder RoadManpadaHiranandani Estate
Mercurrey Hospital serves chronic bladder condition patients from Majiwada, Kapurbawdi, Ghodbunder Road, Manpada, Hiranandani Estate, Brahmand, Owale, and Pokhran Road.Read moreShow less
Patients from Mira Road and Bhayander also attend.
Questions
I have been on antimuscarinics for OAB for 6 months with minimal improvement — could I have IC instead?
Yes — inadequate response to antimuscarinics is one of the clinical triggers for IC assessment. If bladder pain (as distinct from urgency alone) is a significant part of your symptom profile, the diagnosis is more likely IC than OAB. At Mercurrey Hospital, patients with persistent bladder symptoms despite 6 months of antimuscarinics are assessed for IC with cystoscopy before the next OAB treatment tier is applied. Call +91 88280 71522 to arrange reassessment.
Does IC cause pain during intercourse (dyspareunia) and is this addressed at Mercurrey Hospital?
Yes. Dyspareunia is a common and often underreported symptom of IC in women — affecting approximately 50–60% of women with IC. It results from pelvic floor hypertonicity (the pelvic floor muscles tighten in response to bladder pain, causing vaginal discomfort) and from bladder wall sensitivity during deep penetration. At Mercurrey Hospital, the IC assessment specifically asks about dyspareunia and, where significant, coordinates referral to pelvic floor physiotherapy alongside instillation therapy.
How many intravesical instillations are needed for IC and how often do I need to come to Mercurrey Hospital?
The IC instillation induction course involves 6 weekly sessions — one instillation per week for 6 consecutive weeks. Each session takes approximately 30–45 minutes including catheterisation, instillation, 1-hour retention, and discharge. For patients who respond to the induction course, monthly maintenance instillations are continued — typically 6–12 months. Responders often maintain significant benefit with monthly maintenance indefinitely.
Can IC be completely cured or only managed?
IC is a chronic condition — complete cure is uncommon, but sustained symptom control with good quality of life is achievable for most patients who respond to treatment. Approximately 50–70% of IC patients respond meaningfully to intravesical instillation therapy. Some patients experience extended remission — months to years — without ongoing treatment. The instillation treatment can be repeated during any relapse. The goal of IC management is maximising symptom control and quality of life rather than cure.
What is the relationship between IC and bladder cancer — do I still need cystoscopy if I already have a IC diagnosis?
Cystoscopy is both the diagnostic tool for IC and the method for excluding bladder cancer. Bladder cancer must be excluded by cystoscopy before IC treatment is initiated — and cystoscopy for IC diagnosis automatically performs this exclusion simultaneously. However, if haematuria develops in a patient with an established IC diagnosis, a further cystoscopy is indicated to ensure a bladder tumour has not developed alongside the IC. At Mercurrey Hospital, haematuria in an IC patient is assessed with the same urgency as in any other patient.