Overview
The Ghodbunder Road belt's young professional and executive population.Read moreShow less
Men in their 20s and 30s who are building careers and families along the Hiranandani Estate to Brahmand corridor — face testicular cancer with a specific challenge: the research-oriented, health-aware professional who discovers a testicular lump may spend days or weeks online before seeking clinical assessment, which is counterproductive for a cancer where speed of diagnosis is critical. At Mercurrey Hospital in Kapurbawdi, HRG Urology provides testicular cancer assessment for this community at the speed the diagnosis requires — scrotal ultrasound arranged the same week, tumour markers the same day, Cancer Lead specialist review of results as they arrive. Dr. Harshawardhan Godbole FRCS, Cancer Lead. Consultation ₹1,000.
What to know
Testicular Cancer Treatment at Mercurrey Hospital, Kapurbawdi
Testicular cancer is the most common cancer in men aged 15–35 and is highly curable when detected early.Read moreShow less
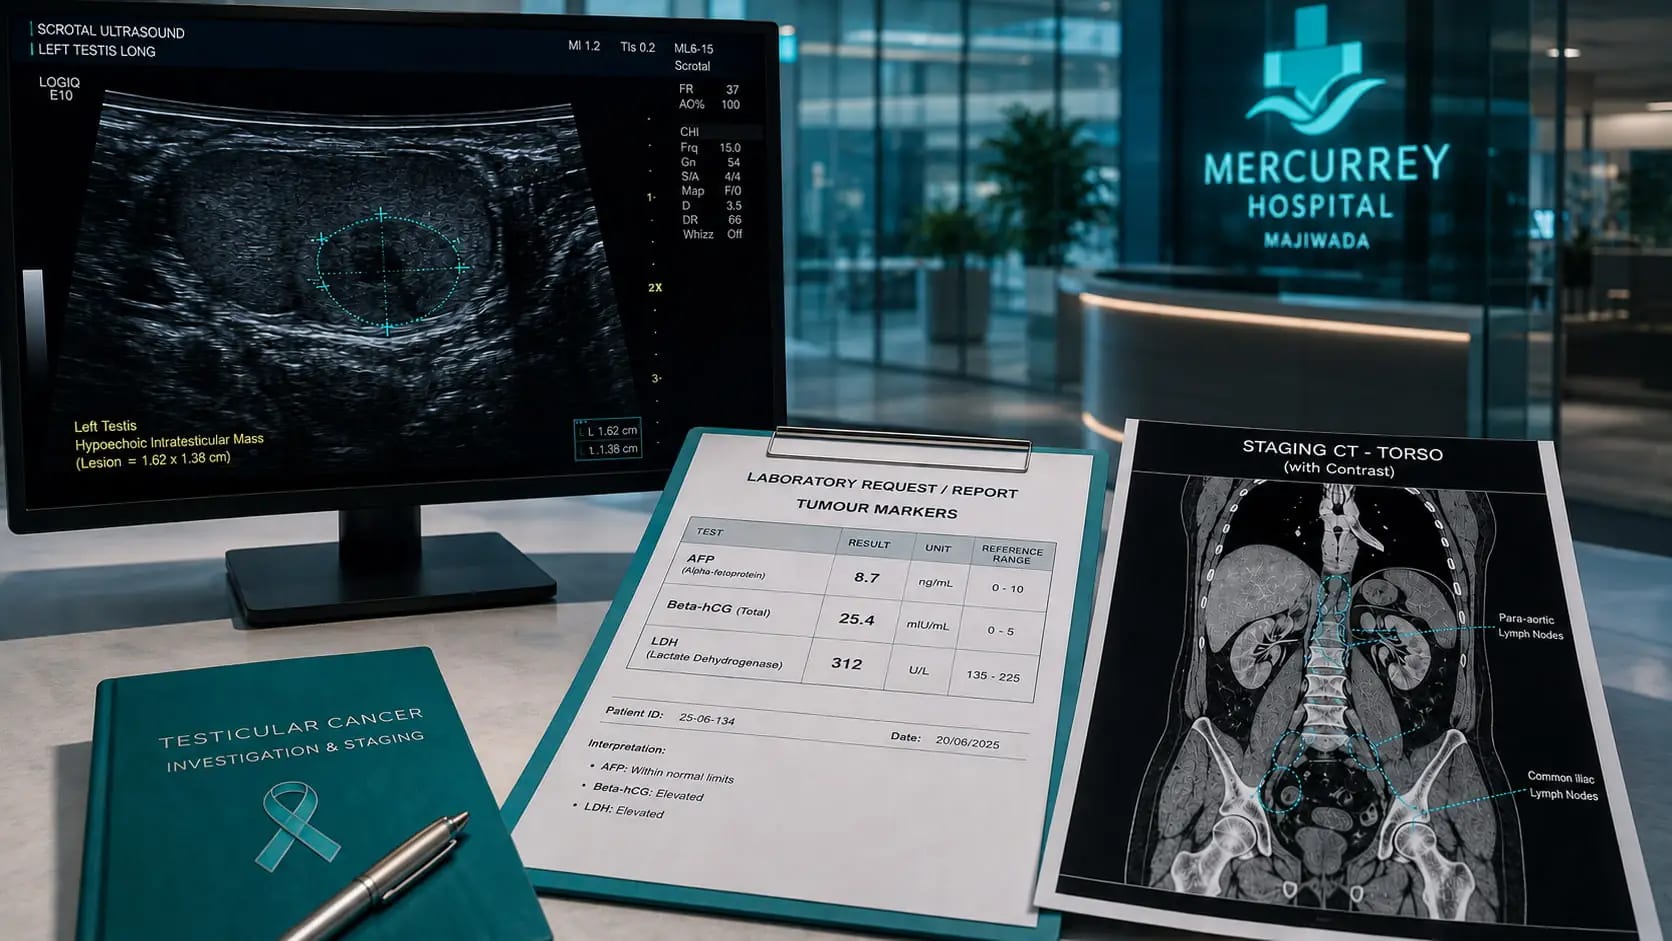
The vast majority are germ cell tumours: seminoma (more common, slower-growing, radio-sensitive) and non-seminoma (embryonal carcinoma, teratoma, choriocarcinoma — faster-growing, requiring chemotherapy). Presentation: minimally invasive testicular swelling or lump, heaviness in the scrotum, or dull ache — occasionally sudden pain mimicking epididymo- orchitis. Investigation: scrotal ultrasound, tumour markers (AFP, beta-hCG, LDH), staging CT. Treatment: orchidectomy (surgical removal of the affected testis) via inguinal incision is both diagnostic and therapeutic. Adjuvant radiotherapy or BEP chemotherapy follows for appropriate stages. Survival for Stage 1 disease exceeds 99%. Dr. Godbole is Cancer Lead and MDT Lead at North Middlesex University Hospital NHS Trust.
Online Self-Research and Testicular Cancer — What the Ghodbunder Road Patient Needs
The Ghodbunder Road professional who discovers a testicular lump will typically spend time researching before attending a clinic.Read moreShow less
Reading about seminoma vs non-seminoma subtypes, tumour markers, and survival rates. This research is understandable but can delay clinical assessment and may cause disproportionate anxiety based on worst-case scenarios. At Mercurrey Hospital, Dr. Godbole's consultation is calibrated to engage with the researched patient — confirming what they have understood correctly, correcting what they have misunderstood (particularly around survival statistics, which are for early-stage disease), and adding the clinical precision that online research cannot provide.
Active Surveillance for Stage 1 Seminoma — The Evidence-Based Option
For Stage 1 seminoma — the most common presentation of testicular cancer at Mercurrey Hospital — three management options exist after orchidectomy: active surveillance (CT and tumour markers at intervals for 5 years), adjuvant radiotherapy (1–2 fractions to retroperitoneal nodes), or adjuvant single-cycle carboplatin chemotherapy.Read moreShow less
All three achieve equivalent survival (>99%). Active surveillance avoids both radiotherapy and chemotherapy side effects but requires consistent follow-up commitment. At Mercurrey Hospital, Dr. Godbole presents all three options with their specific evidence — allowing the Ghodbunder Road patient to make an informed choice between active surveillance and adjuvant treatment.
Travel and Parking Guide – Mercurrey Hospital, Kapurbawdi
High Street Mall Junction, Samata Nagar, Kapurbawdi, Majiwada 400607.Read moreShow less
From Hiranandani Estate: 10–12 minutes. From Manpada: 15 minutes. From Brahmand: 20 minutes. Auto-rickshaws know "Kapurbawdi High Street Mall." Street parking at the junction.
Why Mercurrey
Dr. Godbole's consultation at Mercurrey Hospital engages with the pre-researched Ghodbunder Road patient.Read moreShow less
Providing clinical precision that online research cannot, and correcting the disproportionate anxiety that worst-case scenario reading generates.
The evidence-based three-option discussion for Stage 1 seminoma at Mercurrey Hospital.Read moreShow less
Active surveillance, radiotherapy, or carboplatin — provides the Ghodbunder Road analytical patient with the decision framework they expect from a Cancer Lead specialist.
Nearby areas
MajiwadaKapurbawdiGhodbunder RoadManpadaHiranandani Estate
Mercurrey Hospital serves testicular cancer patients from Majiwada, Kapurbawdi, Ghodbunder Road, Manpada, Hiranandani Estate, Brahmand, Owale, and Pokhran Road.Read moreShow less
Young men from Mira Road and Bhayander also attend this clinic.
Questions
I've been researching online after finding a testicular lump — what should I do next?
Stop researching and call HRG Urology at Mercurrey Hospital on +91 88280 71522 today. Online research for testicular cancer produces disproportionate anxiety from worst-case scenarios that do not apply to early-stage disease, where survival exceeds 99%. The appropriate next step is scrotal ultrasound and tumour markers — not further research. Most testicular lumps in young men are testicular cancer until proven otherwise by ultrasound.
What does scrotal ultrasound show for testicular cancer?
Scrotal ultrasound distinguishes intratesticular lesions (within the testis — which carry a high probability of malignancy) from extratesticular lesions (epididymal cysts, varicoceles — which are usually benign). A solid, hypoechoic (dark) intratesticular mass on ultrasound is testicular cancer until proven otherwise by orchidectomy histopathology. Ultrasound also assesses the contralateral testis for synchronous tumours. At Mercurrey Hospital, scrotal ultrasound is arranged within 48 hours of first contact for any patient with a testicular lump.
What is the inguinal approach for orchidectomy and why is a scrotal approach not used?
Radical orchidectomy is always performed through an inguinal (groin) incision — not a scrotal incision. The reason is lymphatic drainage: the testis drains to para-aortic lymph nodes via the testicular vessels; the scrotal skin drains to inguinal lymph nodes. A scrotal incision risks contaminating the inguinal lymphatics with tumour cells, potentially changing the staging and treatment pathway. Any prior scrotal biopsy or incision on the affected testis must be disclosed at the orchidectomy consultation as it affects subsequent management.
My testicular cancer treatment will need BEP chemotherapy — what side effects should I know about?
BEP chemotherapy (bleomycin, etoposide, cisplatin) causes: nausea and vomiting (manageable with anti-emetics), hair loss (temporary, regrows after treatment), fatigue, increased infection risk (from immune suppression), cisplatin-related kidney and hearing effects (monitored with creatinine and audiometry), and bleomycin-related lung toxicity (lung function tested before each cycle). Fertility impact: sperm production may be reduced for 1–2 years; most men recover fertility after BEP. Long-term cardiovascular risk from cisplatin is recognised and monitored.
Is there a risk of cancer in my other testicle after testicular cancer?
Yes — the risk of a tumour in the contralateral testis is approximately 2–3% over 15 years — significantly higher than the general population risk. Men who had an undescended testis (cryptorchidism) have an elevated risk in both testes. The contralateral testis is examined at diagnosis, and biopsy of the contralateral testis for carcinoma in situ (CIS) is considered in men with specific risk factors (small testis, history of cryptorchidism). Ongoing surveillance includes contralateral testis examination at follow-up visits.